

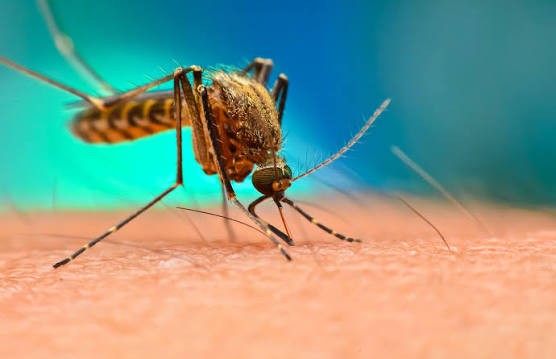
Nearly eight in 10 malaria cases reported in South Africa during the 2025/26 season were imported, with 3 072 of the 3 942 recorded cases originating outside the country, according to provisional figures from the National Department of Health.
While imported infections remain a significant concern, scientists warn that climate change could introduce additional challenges to malaria prevention and control, particularly in vulnerable parts of Limpopo. Researchers say rising temperatures and changing rainfall patterns could influence mosquito populations, malaria transmission and the effectiveness of existing control measures.
“Climate change should increasingly be regarded as an important additional challenge to malaria elimination in southern Africa,” says Professor Tiaan de Jager, the director of the University of Pretoria’s Institute for Sustainable Malaria Control (UP ISMC).
De Jager pointed to two studies published in Nature in 2026 that examine the relationship between climate change and malaria across Africa. One study estimates that climate change could contribute to millions of additional malaria cases and hundreds of thousands of deaths across the continent between 2024 and 2050, with extreme weather events, including flooding, accounting for much of the projected increase.
The second study finds that human-caused warming has probably increased malaria prevalence in southern and eastern Africa, although the effects differ across regions. However, De Jager cautions against assuming that higher temperatures will automatically lead to increased malaria transmission everywhere.
Very high temperatures can reduce the survival of mosquitoes and malaria parasites, while heavy rainfall can wash away potential mosquito breeding sites.
“The most recent research suggests that the climate-malaria relationship is more complex than simply saying ‘warmer temperatures mean more malaria’,” he says.
He expects much of the potential increase in malaria transmission to occur in areas where the disease is already established, rather than through widespread expansion into entirely new areas.
Why Limpopo matters
Within South Africa, malaria risk is concentrated in the north-east, particularly Vhembe District and the Limpopo River Valley, according to De Jager. The area presents several challenges for malaria control, including suitable mosquito habitats, rivers, irrigation systems, agricultural activity, rural communities with limited access to healthcare and movement across neighbouring countries.
“The Limpopo River is not simply a geographical boundary,” he says. “It is also an ecological and epidemiological corridor.”
De Jager also points to the possibility of a longer malaria transmission season as climatic conditions change, potentially extending risk into June and July.
Such a development could present additional challenges for communities and health authorities that have traditionally experienced lower malaria transmission during the winter months.
What the Health Department says
The National Department of Health says it monitors changes in malaria cases, seasonal patterns, transmission areas and geographical spread through its Malaria Information System. According to the department, malaria cases must be notified within 24 hours and investigated within 72 hours to support timely public health interventions.
Any locally acquired case detected in a historically low-risk area should trigger an investigation and targeted response. These measures include active case detection, vector assessments, mosquito control and community mobilisation. However, the figures provided by the department are national totals. It did not provide a breakdown of the 2025/26 cases specifically for Limpopo.
On the availability of resources, the department says these could be reprioritised when flooding or other extreme weather events increase transmission risks or disrupt spraying operations, surveillance and access to healthcare services.
Its message to communities remains clear: “Malaria is preventable and curable, but delayed treatment can be fatal.”
Residents experiencing symptoms such as fever, chills or body pains are encouraged to seek medical attention immediately and inform healthcare workers about any recent travel, particularly to malaria-risk areas.
The realities facing communities in Vhembe
Taneshka Kruger of the UP ISMC has worked with rural communities in Vhembe, where she says awareness of malaria does not always translate into effective prevention. Although many residents understand that mosquitoes transmit malaria, their ability to protect themselves can be limited by economic and practical circumstances.
“Knowing how to prevent malaria does not necessarily mean people have the resources or opportunity to act on that knowledge,” says Kruger.
She identifies financial constraints, limited access to prevention supplies, housing conditions and distance from healthcare facilities as some of the barriers facing rural communities. Kruger also warns that malaria awareness campaigns do not always reach remote communities, mobile populations and people working outdoors.
She believes prevention efforts should involve sustained community engagement rather than relying mainly on seasonal awareness campaigns. However, she cautions against treating community observations as scientific confirmation of changing malaria transmission patterns.
“Community observations alone cannot confirm shifts in transmission patterns,” she says. For Kruger, one of the most important priorities is closing the gap between malaria awareness and the ability to take preventive action.
“Communities need more than information; they need the means and support to act on it,” she says.
Who is most vulnerable?
De Jager identifies rural communities with limited access to healthcare, agricultural and outdoor workers living or working near rivers and people who regularly cross national borders as groups that may face increased exposure.
He also highlights the broader socioeconomic dimension of the disease, particularly its impact on vulnerable communities.
“Malaria is a disease of poverty and is preventable and curable,” he says, adding that a child under five dies from malaria every minute globally.
Towards more predictive malaria control
The UP ISMC is working on approaches that could help health authorities anticipate changing malaria risks. The proposed climate-informed malaria control system would combine satellite information, weather forecasts, mosquito surveillance, malaria case data and population movement patterns to identify areas facing increased risk.
The institute is also working with the Department of Health on a malaria application intended to provide information to communities and travellers. De Jager says these approaches could help health authorities identify environmental and climatic conditions associated with increased malaria risk before cases begin to rise.
“Instead of waiting for malaria cases to increase and then responding, we should increasingly be able to identify environmental and climatic conditions that indicate elevated risk weeks or months in advance,” he says.
He believes the future of malaria prevention will depend increasingly on early warning systems, improved surveillance and stronger community-level interventions.
“The future of malaria control should be predictive rather than reactive,” adds De Jager.









